
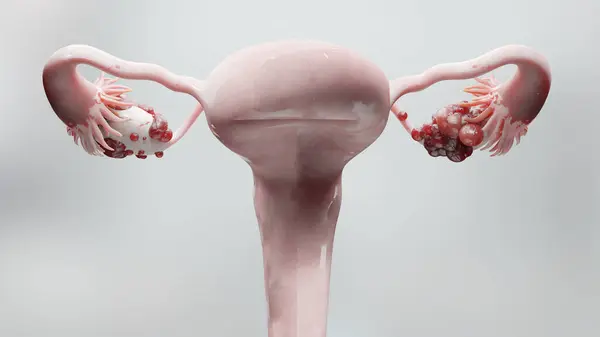
An ovarian cyst is one of those diagnoses whose very name is often frightening. Many women who hear it after an ultrasound scan immediately think of surgery, infertility or cancer. Others, on the contrary, reassure themselves so thoroughly with “it’s very common” that they stop taking the situation seriously at all. Both extremes usually lead in the wrong direction. In reality, an ovarian cyst is not one specific condition but a range of very different growths, and everything depends on which one it is: whether monitoring is enough, whether treatment is needed, whether you need to act quickly.
In modern gynaecology the key question is not “I have a cyst, what now?” but “What kind of cyst is it, how is it behaving and does it pose any risks?” This is what separates a calm, rational approach from unnecessary fears or, conversely, dangerous delay. Most cysts in women of reproductive age turn out to be benign, and many of them disappear on their own without treatment. But there are other cases in which simply waiting is no longer enough.
What exactly is an ovarian cyst?
An ovarian cyst is a sac or cavity filled with fluid or other contents that forms in the ovary or on its surface. Some cysts are functional, meaning they are linked to the normal work of the ovary during the menstrual cycle, and these are the ones that are most often temporary. Other cysts may be non-functional, meaning they are not directly linked to ovulation, and these more often need closer monitoring or a different approach.
It is very important to understand that the word “cyst” on its own says nothing about how dangerous it is. The same term can describe a small functional cyst that will disappear within a few cycles and a cyst that will need to be removed. That is why a good doctor never stops at “you have a cyst” but explains its type, size and structure and what should happen next.
When may an ovarian cyst not need treatment?
In many cases, at least at the outset. Mayo Clinic, Cleveland Clinic and the NHS state plainly that many cysts, especially functional ones, can disappear on their own. So the first step is often monitoring: a repeat ultrasound after a certain time, an assessment of symptoms and tracking of any changes. This is not “doing nothing” but an entirely normal medical approach if the cyst looks benign, is small and is not causing significant symptoms.
This applies especially to simple cysts in women before the menopause. NHS clinical guidance in Scotland notes that simple cysts smaller than 5 cm in premenopausal women often resolve within 2–3 menstrual cycles without any intervention. That is why not every cyst found on ultrasound means treatment straight away. Sometimes the right first choice is to give the body time and see whether the cyst shrinks or disappears.
When is monitoring the right approach rather than a waste of time?
Monitoring is justified when the doctor sees a low probability of a dangerous process. These are usually situations in which the cyst has a simple structure, has no suspicious features on ultrasound, is not causing significant pain and is not growing quickly, and the patient is not postmenopausal and has no other risk factors. In these cases a repeat ultrasound after a few weeks or months helps to show whether the cyst is behaving like a functional one, that is, shrinking, or whether it stays the same or grows.
This is where many women make one of two opposite mistakes. The first is to panic if the doctor does not offer surgery straight away. The second is to decide that if only follow-up has been arranged, the situation does not matter at all. In fact, follow-up is part of the treatment plan. It is needed not because the doctor is unsure, but because how a cyst changes over time often gives more information than a single scan on a particular day of the cycle.
Which symptoms may suggest that monitoring is no longer enough?
Pain is the most common warning sign. A cyst can cause a dragging or aching pain in the lower abdomen, a feeling of pressure or heaviness, bloating, discomfort during sex and sometimes symptoms linked to pressure on the bladder or bowel. The NHS and Mayo Clinic also mention possible changes to the cycle, a feeling of fullness, frequent urges to pass urine and pelvic discomfort. If these symptoms persist or get worse, simple monitoring is not always the right option.
Sudden severe pain needs a separate mention. If a cyst ruptures, bleeds or causes the ovary to twist (torsion), the pain can be sharp and intense. Situations like these are no longer about routine follow-up but about urgent assessment. That is why it is important not only to know that you have a cyst but also to understand which symptoms are acceptable and which call for an urgent response.
When is treatment needed even if the symptoms are not severe?
There are several scenarios in which a more active approach is considered even without dramatic symptoms. The first is when the cyst does not go away over time and does not look functional. The second is when it is getting bigger or has a complex or atypical structure. The third is when the patient is postmenopausal, because in this group the approach to cysts is more cautious, as doctors are more alert to the possibility of cancer. NHS inform states plainly that the decision depends on the size and appearance of the cyst, the symptoms and whether the menopause has taken place.
Sometimes treatment is also needed if the cyst complicates plans for pregnancy or raises doubts about its nature. So it is not always about how severe the pain is. Sometimes the main reason for a more active approach is clinical uncertainty, or the risk that simply waiting will not lead anywhere useful.
Can a cyst be treated without surgery?
In some cases, yes, but honesty matters here. If a cyst is functional and very likely to disappear on its own, “treatment” often means monitoring rather than tablets. Cleveland Clinic states plainly that watchful waiting is the usual first approach, with a repeat ultrasound used to see whether the cyst is shrinking or changing.
At the same time, it is worth not overestimating the role of medication. Many women believe there is a pill that will “dissolve” any cyst. In reality things are much more complicated: not every cyst responds to conservative treatment, and not every cyst needs medication. That is why the modern approach is not a one-size-fits-all regimen but is based on the type of cyst and the clinical picture.
When does surgery become a question?
Surgery is most often considered when a cyst is large, causes symptoms, does not go away, changes its appearance, has complex features or raises the suspicion that it is not a functional cyst. Mayo Clinic states plainly that surgical removal may be needed if the cyst is large, growing, does not look functional or causes pain.
It is important not to be automatically afraid of the word “surgery”. In modern gynaecology it is often not a large open abdominal operation but a laparoscopic, that is, minimally invasive, procedure, if the situation allows. So the question is not “is it frightening” but whether surgery will do more good than continued monitoring. If the answer is yes, putting it off purely out of fear can sometimes be less safe than having a planned operation.
How do age and the menopause affect the decision?
Very significantly. In women of reproductive age a large proportion of cysts are functional and benign, so monitoring is used much more often. After the menopause the approach is more cautious, because the appearance of a cystic growth is assessed in a different clinical context. NHS inform specifically emphasises that menopausal status is one of the key factors in deciding on the approach.
That is why two women with similar-looking cysts may receive different recommendations, and this is not a contradiction but normal clinical reasoning. What matters is not just the ultrasound report but the whole context: age, symptoms, medical history, risks and plans for pregnancy.
Why you should not decide for yourself that “it’s just a functional cyst”
Because the ultrasound description, the clinical context and changes over time all matter together. What a woman has read online about “common functional cysts” does not mean that her situation fits that scenario. And conversely, the word “cyst” on its own does not automatically mean surgery. Decisions made on your own are almost always worse than a professional assessment, because they are based either on unnecessary fear or on excessive reassurance.
The most sensible approach is not to guess but to understand together with your doctor which type of cyst is suspected, how big it is, whether it has benign features, what follow-up is needed and which symptoms should change the plan. That way you come away not with anxiety but with clarity.
Why coordination through MediUkraine matters for international patients
When a patient is coming from abroad, an ovarian cyst becomes not only a medical question but a logistical one. You need to know whether you can start with a remote consultation, whether your existing ultrasound and test results are sufficient, whether you need to travel only for follow-up, or whether there are already grounds to consider treatment. This is where the value of a coordination service such as MediUkraine is especially clear: it does not just find a gynaecologist but builds the whole pathway, from reviewing your documents to a clear plan for monitoring or treatment, with the EXPERT medical network in Uzhhorod, whose team communicates with international patients in English.
For you, this means less confusion and fewer unnecessary steps. Instead of interpreting the ultrasound report yourself, searching for a clinic at random and getting lost among conflicting advice, you get a structured process with a clear logic, sequence and decision criteria.
01Conclusion
An ovarian cyst is not automatically a reason for surgery, nor is it a symptom to be ignored without thinking. In a great many cases monitoring really is the right decision, especially if the cyst is simple, small and not causing significant symptoms. But there are situations in which active treatment is needed: if the cyst does not go away, is growing, is painful, has a complex structure or raises doubts about its nature.
The strongest position here is not to be frightened by the word “cyst” and not to reassure yourself too quickly. Rather than guessing, you need to understand exactly what has been found and how it is behaving. That is how modern gynaecology works. And if this pathway is organised through MediUkraine, you get not just a consultation but a clear route, from the first ultrasound to a decision that genuinely fits your situation.




